In the United States, patients are waiting longer for cancer surgery than they did in the past
What's this about?
People disagree about whether U.S. cancer patients now wait longer for surgery than before.
The answer seems yes in many cases, but not for every patient or cancer type.
What supporters say
- A new study using U.S. data found that cancer surgery waits grew over about ten years.
- Lung cancer studies show that doctors can track waits across the country.
- During the COVID-19 crisis, many patients waited longer for cancer surgery.
- Some health care groups saw surgery waits get worse.
What critics say
- The longer waits do not appear in every part of the country or for every cancer type.
- The change may partly come from shifts in the kinds of cases and care doctors see.
How to read this
The number of points on each side does not show who is right; stronger proof matters more.
The bottom line
The evidence leans toward longer cancer surgery waits in many U.S. settings.
But we are not sure how much waits grew, or how widely this trend reaches.
The available evidence suggests that U.S. cancer patients have, in many settings, waited longer for surgery than in the past. But the size and reach of that increase remain uncertain: the pattern is clearest in certain cancers, health systems and periods, rather than among every patient nationwide.
The case for
The strongest support comes from a recent national U.S. study that directly examined changes in cancer-surgery waiting times over roughly the past decade. It reportedly found that waits increased. Because the study used national data and addressed the historical trend itself, it is more persuasive than reports from individual hospitals. However, the available information does not give the exact size of the increase, the cancers included or the full study period. 1
The COVID-19 pandemic provides separate evidence that cancer surgery became harder to access. Studies reported longer waits for breast-cancer and endometrial-cancer surgery, along with broader slowdowns in cancer operations. These findings show that patients waited longer during a major disruption, although they do not by themselves prove that waits continued to rise after the health system recovered. The endometrial-cancer research, for example, came from a single institution. 2
Research on lung cancer offers another national example. Studies of U.S. patients have measured the time from diagnosis to surgery and examined differences linked to access and other patient characteristics. That work supports the view that waiting times can be tracked nationally and that delays are not experienced equally. The supplied evidence does not, however, provide the exact national increase over time. 3
A Department of Veterans Affairs research brief also reported longer waits for surgical cancer treatment, particularly within VA hospitals. This adds evidence from a large health system, but VA patients and hospitals may not reflect care across the broader U.S. system. Some individual health systems have likewise reported worsening waits, though such reports are weaker evidence of a national trend. 4
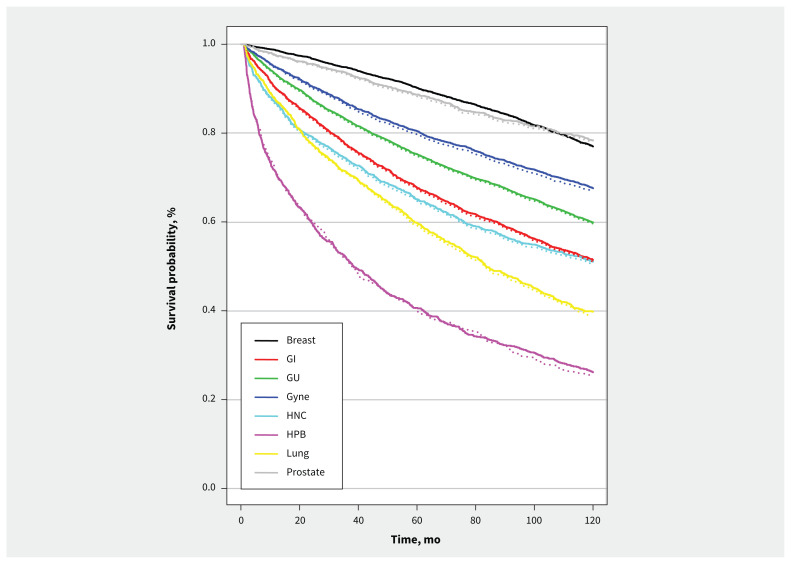
The issue matters because delays can affect outcomes. A review of breast-cancer studies found that longer waits before surgery were associated with poorer survival, while reviews of thoracic cancers raised concerns about delayed and uneven treatment during the pandemic. These studies explain why an increase in waiting time could be important, but they do not prove a nationwide historical rise.
The case against
The main challenge is scope. Much of the evidence concerns particular cancers, hospitals or pandemic conditions. It does not establish that every U.S. patient, cancer type or form of surgery has faced longer waits. Even a large national registry is not a complete census of all cancer care, and its recorded intervals may not capture every part of a patient’s experience. 5
There is also a question about what the numbers measure. Treatment choices and the types of patients receiving surgery have changed over time. A National Cancer Database study found major changes in treatment patterns for early-stage lung cancer between 2004 and 2013. If the population selected for surgery changes, the average time from diagnosis to surgery may change as well, without representing a uniform decline in access. 6
National averages can also hide important differences. Waiting times may vary by race, income, geography, insurance coverage and hospital. A modest national increase could coexist with much longer waits for some groups, while some communities or hospitals may have improved.
The bottom line
The evidence favors the claim, but only moderately and with important limits. A strong national study directly reports that cancer-surgery waits increased, and cancer-specific and pandemic-era research provides meaningful support. That makes it more likely than not that U.S. patients have waited longer in important settings and periods.
The evidence is much less conclusive on whether the increase is permanent, applies to every cancer or patient, or reflects a broad deterioration in access. The key unanswered questions concern the national study’s exact estimates, the cancers and patients it covered, and whether its results extend beyond pandemic disruption. Changes in treatment patterns, registry coverage and patient mix may also explain part of the measured rise.
Figures & data
All contributions are reviewed for clarity, balance, and evidence. The strongest insights are elevated into the argument graph — with credit to you.
Help improve this analysis →